
Periwound Necrosis
The trained eye is the first dressing a wound recieves (nurse zed)
For any sign of periwound tissue necrosis ito ang framework sa isip ko kaya madalas di ako nagsasalita kapag nag open tayo ng dressing dahil kailangan masagot muna ito;
- cause of necrosis? pressure ba? nutrition ba? electrolytes ba?
- superficial or deep tissue? this is specially important sa meron undermining more than 3cm
- perfusion intact or not? meron ba tayo probable hindrance that will impede wound healing?
- tissue behavior? ano ba galaw nya? starting or advancing na?
- inflammation stage due to which factors?
- healabilty matrix? anong klaseng sugat ba ito?
- odour? san galing? localize or malalim?
- Quality ng exudate? gaano kalapot at labnaw para dun natin iaayon ang dressing selection?
Once mahanap na natin ang sagot then saka tayo mag recommend ng possible dressing approach para ma relate natin ng maayos sa diagnosis ng doctor.
Ito ang mahalaga kapag guided tayo ng medical doctor kasi nabibigay ng maayos ang clinical sign at na translate ng maayos and eventually na resolve yung medical concern na na identify natin. With this case, si Dr. Reynaldo Salinel Jr. ang ating partner.
Si patient ay nasa 12 months na natin nilalagyan ng NPWT somewhere in Manila, SCI, late 50s, male.
Isa rin sila sa biktima ng maling wound management which they resorted to a lot of things na rin gaya ng povidone iodine the wrong way, bleach and 3rd solution, soap and water, dressing misinformation etc.
Meron syang trochanter right side pressure injuries, and 9 inches away naman ang kanyang gluteal folds ay meron din. and sadly sa kabilang side, left side na gluteal folds ay meron din both share the same depth of 5cm with 2 tunneling wound with depth of 3cm. We are able to close the 1st tunnel and now isang tunnel na lang both ang issue and still managing it through NPWT.
With trochanter right side medyo mahihirapan tayo ipaclose agad due to mechanical pressure the muscle endure during sitting and feedback which affect the integrity of the tissue to bind. Hindi rin naman pwede sabihan si patient na higa kana lang para gumaling na since it will compromise his food intake and baka magkaroon pa ng aspiration pneumonia.
This is dated 29September26 during our schedule dressing change and pinahinto muna ang NPWT since the odour, the tissue, and localize infection, and panay ang change dahil sa leak ng malapot na exudate kaya nag reseta si doc ng antibiotic.
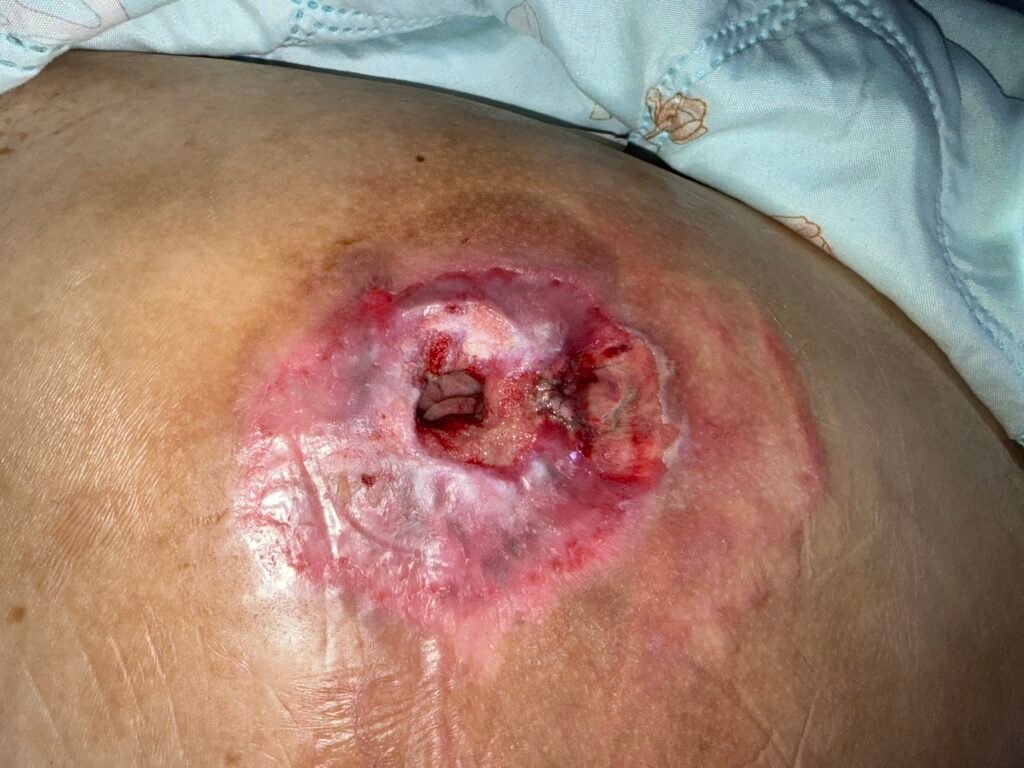
if papansinin nyo rin ang erythema sa periwound ay nagsisimula na kaya kailangan na itong bigyan ng medical attention kaya stop NPWT then regular dressing muna tayo ng silver aglinate na ipapasok sa loob ng sugat and silver dressing FOAM naman sa area na meron periwound necrosis. Bakit kailangan FOAM dressing na meron SILVER ang gamitin? From the tissue presentation, 1 wrong product will eventually ruin the tissue and mabutas ito which add problem. Ang main focus natin ay magkaroon ng absorption and since meron sign ng localize infection kaya nag silver din tayo and to abosrb all moisture na rin. After 1 week ito na ang result.
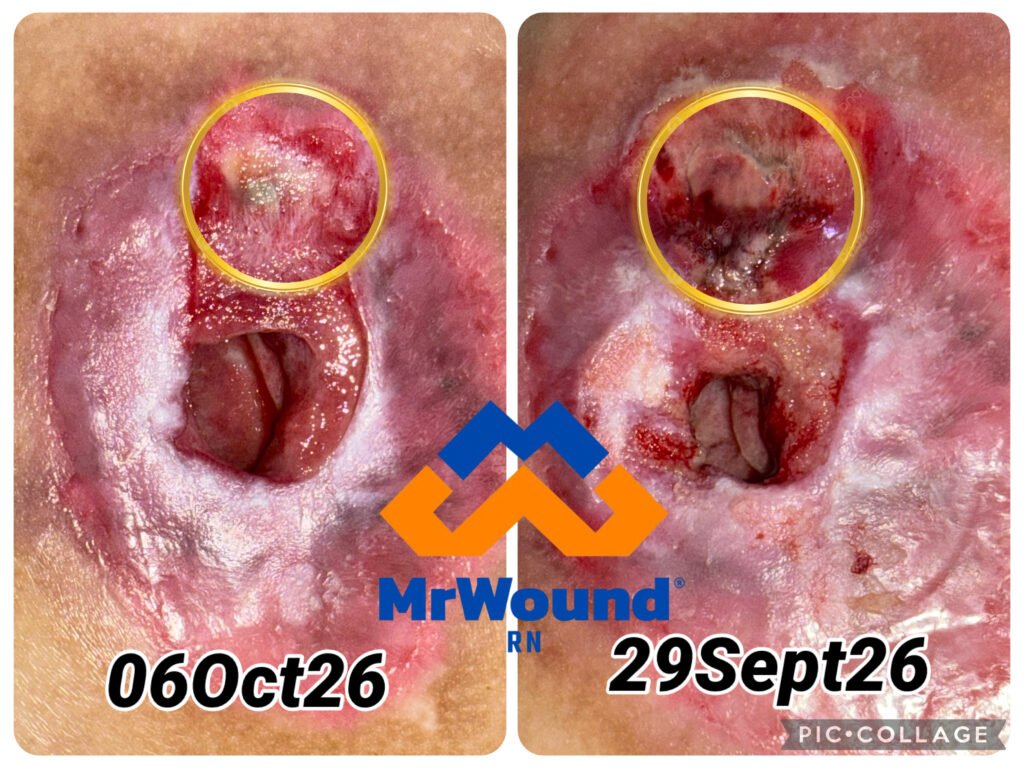
Mahirap lagyan ng povidone iodine ito dahil baka mabutas and so far as per evidence based ito lang un alternative natin. Nakakalungkot lang ano kasi hindi lahat ng ating mga kababayan ay may access sa ganitong consumable.
Yesterday nilagay na rin natin ang NPWT though meron pa sign ng maceration sa edges na potentially magka issue which trained naman ang asawa to troubleshoot.
Bottomline, ang dressing na ginamit natin sa tunneling wounds ay silver alginate, sa periwound necrosis ay silver FOAM dressing, and PRONTOSAN for antibiofilm and Langgas formula natin, and same pa rin following the moist wound environment.
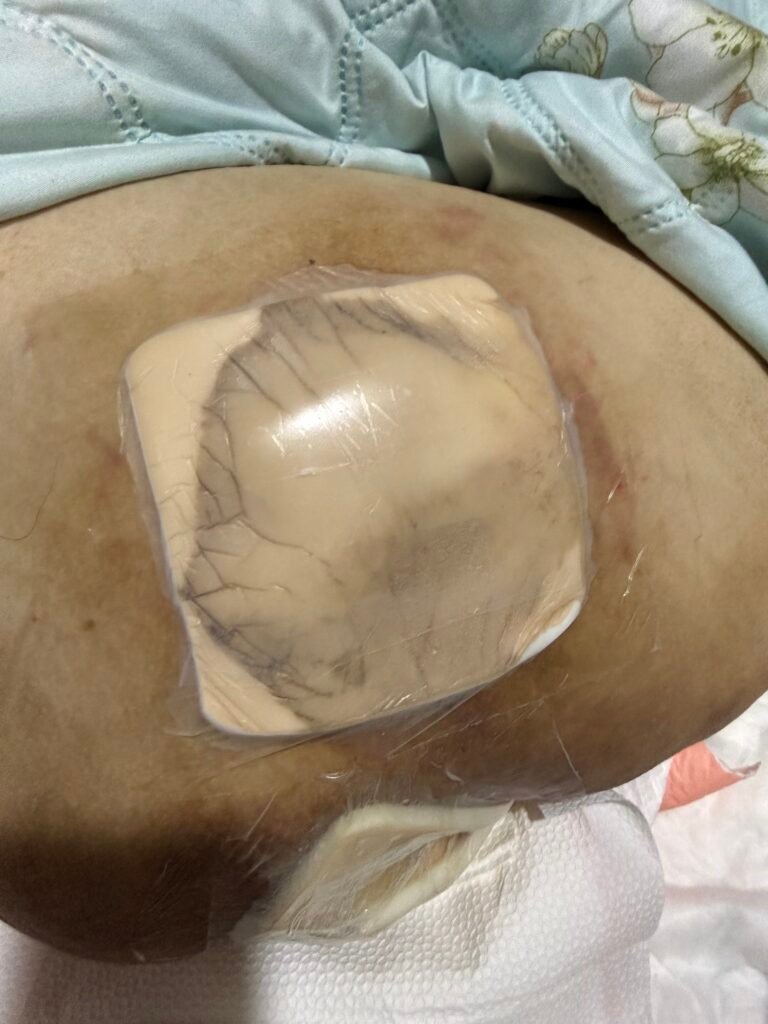
This is the regular foam dressing their using, sarili nilang supplies ito para makamura sila. when this type of exudate and the mancha its time to change the dressing. So far once a day talaga nila pinapalitan or BID or two times daily depende sa galaw ng sugat.
Ingat lagi mga ka sugat!
Nurse Armzed aka. MrWound
